

Weight Loss Resistance Explained: What The Research Supports, What It Doesn’t, And What To Do Next
Jim Wendler
Strength coach, On Consistency
Make time for it. Just get it done. Nobody ever got strong or got in shape by thinking about it. They did it.
Summary (TL;DR)
Weight loss resistance is a non-medical term for when you’re eating less and moving more, but the scale barely moves. It isn’t an official diagnosis. The causes with the strongest evidence are metabolic adaptation, underestimated intake, insulin resistance, an underactive thyroid, weight-promoting medications, poor sleep and the menopause transition. Rule those out before you chase detoxes or supplements.
You’ve cut portions, you’re walking every day, and you’ve weighed yourself every morning for three weeks. The number hasn’t changed. Maybe it’s gone up. At some point a search bar suggests the phrase “weight loss resistance,” and it feels like a relief: finally, a name for what’s happening.
The name is useful. Some of what gets sold under it isn’t. Search the term, and you’ll mostly find clinics and coaches listing ten or twelve “hidden causes”: estrogen dominance, leptin resistance, gut imbalance. Many come with a test kit or a protocol attached. Some of those causes are real, well-measured and fixable. Others rest on thin evidence.
This guide sorts them for you. Each cause is graded by the strength of the research behind it, so you know what to ask your doctor about first, what’s worth tweaking at home, and what you can safely stop worrying about.
Medical & Referral Disclaimer
This article is for general education and isn’t medical advice. If you have unexplained weight gain, new fatigue, irregular periods, or you take prescription medication, talk to your doctor before changing your diet, training or supplements. Don’t stop or change any medication without medical guidance.
Key Takeaways
- It’s a description, not a diagnosis. “Weight loss resistance” describes a frustrating pattern. It doesn’t name one condition.
- Your metabolism does slow when you diet. Metabolic adaptation is real and measurable, but it doesn’t stop fat loss on its own.
- Tracking gaps are the most common hidden factor. In a classic study, “diet-resistant” people underreported food intake by nearly half.
- Some medical causes need a blood test. Thyroid function and blood sugar markers are simple to check and worth ruling out.
- Some women are truly resistant. Over a quarter of midlife women in one specialist clinic lost under 5% in a year of care, so ask about medical options if the basics don’t work.
- Midlife changes the target. During the menopause transition, fat gain speeds up and lean mass drops, even when weight stays flat.
- Sleep and strength training protect muscle. Both help more of the weight you lose come from fat.

What Is Weight Loss Resistance?
Weight loss resistance is when you consistently follow a calorie deficit and still lose little or no weight over several weeks. It’s a popular label rather than a medical diagnosis, and it usually has one or more identifiable causes behind it.
The idea isn’t new. Back in 1992, researchers studied people who reported eating under 1,200 calories a day without losing weight. They called it “diet resistance.” You’ll see what they found in a moment, and it’s the best place to start.
For now, keep one thing in mind: a label that describes your frustration accurately doesn’t tell you the cause. That’s the job of the rest of this guide.
Treatment-Resistant Obesity: The Clinical Version
The closest medical term is “treatment-resistant obesity” (TRO): losing less than 5% of body weight after a full year of specialist obesity care. Researchers only began studying it in midlife women recently, and the early findings are useful.
A 2026 study from Virginia Commonwealth University reviewed the records of 203 women aged 40 to 60 with obesity. More than 27% met the definition of treatment-resistant obesity despite a year of expert care.
Women who didn’t use FDA-approved injectable weight loss medications were about 3.5 times more likely to be resistant, and those who didn’t lower their carbohydrate intake were about twice as likely.
Two caveats matter. This was one clinic looking back at records, not a trial, and those two factors explained only a small part of the difference between women. Still, it confirms what many of you already feel: for some women, resistance is real, and it isn’t a willpower problem.
Weight Loss Resistance vs A Weight Loss Plateau
A plateau is a stall after a period of steady weight loss, while weight loss resistance usually describes struggling to lose from the start. The two overlap, and many of the same causes drive both.

| Feature | Weight Loss Plateau | Weight Loss Resistance |
|---|---|---|
| When it shows up | After weeks or months of successful loss | Often from the start of a new plan |
| Typical driver | Lower energy needs at a smaller body size; metabolic adaptation | Intake higher than tracked, medical factors, medications, sleep, midlife changes |
| First step | Recalculate your calorie needs at your new weight | Audit your tracking, then ask about blood tests and medication side effects |
| Is it a diagnosis? | No | No |
If you’ve already lost a good amount and stalled, our guide on how many calories you should be eating will help you reset your numbers.
Weight Loss Resistance Causes, Graded By Evidence
The causes with the most solid research are metabolic adaptation, underestimated intake, insulin resistance, hypothyroidism, weight-promoting medications, short sleep and the menopause transition. Popular causes like estrogen dominance and leptin resistance have far weaker evidence as everyday explanations.
Here’s how the common causes stack up. “Strong” means well-measured human studies or official medical guidance. “Moderate” means real but smaller or less direct evidence. “Weak” means the idea is plausible but not established as a practical explanation you can test and fix.
| Cause | Evidence Strength | How You’d Check It |
|---|---|---|
| Underestimated food intake | Strong | Weigh and log everything for 14 days |
| Metabolic adaptation | Strong | Expected with dieting; adjust targets as you lose |
| Insulin resistance / prediabetes | Strong | A1C or fasting glucose blood test |
| Hypothyroidism | Strong | TSH blood test |
| Weight-promoting medications | Strong | Medication review with your doctor |
| Menopause transition | Strong | Cycle changes, age, symptoms |
| Short sleep | Moderate | Track sleep for two weeks |
| Chronic stress and cortisol | Moderate | Honest stress audit; no reliable home test |
| Inflammation | Weak to moderate | No single useful test for weight purposes |
| Leptin resistance | Weak (as a practical diagnosis) | No validated routine clinical test |
| “Estrogen dominance” | Weak | Not a recognised diagnosis in mainstream medicine |

1. Your Intake Is Higher Than You Think
The single most common hidden cause is eating more than your food log shows. It isn’t dishonesty. Portion sizes, oils, drinks, tastes while cooking and weekend meals are genuinely hard to estimate.
That 1992 “diet resistance” study is the clearest proof. The people who said they couldn’t lose weight on under 1,200 calories had normal metabolisms, within 5% of predicted values.
But when researchers measured what they actually ate, they had underreported their food intake by an average of 47% and overreported their physical activity by 51%. The researchers concluded that the problem wasn’t a broken metabolism.
This isn’t about blame. It’s good news, because it’s the most fixable cause on the list. Try this for two weeks:
- Weigh foods on a kitchen scale instead of estimating with cups or spoons.
- Log cooking oils, dressings, sauces and milk in coffee.
- Count drinks, including wine, juice and smoothies.
- Track weekends as carefully as weekdays.
- Log bites and tastes, even if they feel too small to matter.
2. Metabolic Adaptation: Your Body Pushes Back
Yes, dieting slows your metabolism, and often by more than your smaller size alone explains. This is called metabolic adaptation, and it’s one reason fat loss gets harder the longer you diet.
The most famous example comes from former contestants of “The Biggest Loser.” After the 30-week competition, their resting metabolic rate had dropped by about 610 calories a day. Six years later, it was still around 700 calories a day below where it started, and about 500 calories lower than expected for their body size.
Keep that in context, though. Those contestants lost an average of 58 kg through extreme diet and exercise. Most women trying to lose 5 to 10 kg won’t see anything close to that. The practical lessons:
- Recalculate your calorie target every 4 to 5 kg lost.
- Avoid very aggressive deficits, which push harder against your body’s defences.
- Build or keep muscle, which helps protect your resting energy use.
- Plan occasional maintenance weeks so the diet is sustainable.

3. Insulin Resistance And Blood Sugar
Insulin resistance means your body doesn’t respond to insulin properly, and it’s linked to both higher blood sugar and weight gain. It’s common, often silent, and easy to screen for.
According to the National Institute of Diabetes and Digestive and Kidney Diseases, insulin resistance can lead to increased blood sugar levels and weight gain. Prediabetes is diagnosed with an A1C between 5.7% and 6.4%, or a fasting glucose of 100 to 125 mg/dL. The good news is that it responds well to weight loss and regular physical activity.
If you have a family history of type 2 diabetes, polycystic ovary syndrome, or carry more weight around your middle, ask your doctor for an A1C test.
4. Thyroid Dysfunction
An underactive thyroid (hypothyroidism) can cause weight gain, fatigue and feeling cold, and it’s much more common in women. A simple TSH blood test can check for it.
The NIDDK notes that women are much more likely than men to develop hypothyroidism, and it becomes more common after 60. Symptoms include tiredness, weight gain, dry skin and hair, and heavy or irregular periods. Many of those overlap with perimenopause, which is exactly why a test beats guessing.
One caution: taking thyroid medication you don’t need won’t fix weight loss resistance. In that same 1992 study, the “diet-resistant” group used thyroid medication at a high rate, and it didn’t explain their results. Treat a diagnosed problem, not a hunch.
5. Medications That Promote Weight Gain
Some common prescriptions make weight loss harder, and your doctor can often suggest a weight-neutral alternative. Never stop a medication on your own.
The Endocrine Society’s clinical guideline on obesity points out that many medications for diabetes, depression and other chronic diseases affect weight, and recommends choosing drugs with favourable weight profiles where possible. If your struggle started around the time you began a new medication, bring that timeline to your next appointment.
Weight Loss Resistance In Perimenopause And Menopause
During the menopause transition, fat gain roughly doubles in speed and lean mass starts to decline, even if your weight stays about the same. That’s why many women over 40 feel “resistant” when their body is actually changing shape.

The Study of Women’s Health Across the Nation (SWAN) tracked women’s body composition for years. It found that at the start of the menopause transition, the rate of fat gain doubled and lean mass declined. These changes continued until about two years after the final period, then levelled off. Weight itself climbed steadily before menopause without a sudden jump.
This changes what “success” looks like in your 40s and 50s. The scale can hide real progress or real problems. Better markers include:
- Waist measurement, taken monthly at the same spot.
- Strength numbers in the gym.
- How your clothes fit.
- Energy, sleep quality and hunger levels.
For a deeper look at this stage, read why it’s so hard to lose weight in perimenopause.
Sleep, Stress And Cortisol Levels
Short sleep and chronic stress don’t block fat loss outright, but both shift your results in the wrong direction. Sleep has stronger evidence than the other.
Short Sleep Changes What You Lose
When you sleep too little during a diet, more of the weight you lose comes from muscle and less from fat. This is one of the clearest lifestyle findings in the research.
In a controlled trial, people followed the same reduced-calorie diet with either 8.5 or 5.5 hours in bed. With less sleep, the proportion of weight lost as fat fell by 55% and loss of lean mass rose by 60%. They were also hungrier. It was a small, short study, but the direction is hard to ignore. Our guide on how sleep affects weight loss in women has practical fixes.
Chronic Stress And Belly Fat
Women who store more fat around the middle tend to release more cortisol under stress, but cortisol is one factor among many, not a master switch. Stress also affects sleep, cravings and motivation, which matter just as much.
In a study of 59 premenopausal women, those with a higher waist-to-hip ratio secreted more cortisol during stressful tasks and reported more chronic stress. That’s a link, not proof that cortisol alone causes belly fat.
There’s no reliable home test for “high cortisol,” so be wary of anyone selling one as the answer. If you want to know how stress-related weight differs from hormonal changes, see cortisol belly vs hormonal belly.

The Popular Causes With Weaker Evidence
Leptin resistance, “estrogen dominance,” inflammation and gut imbalance are real research topics, but none is a proven, testable explanation for everyday weight loss resistance. That’s why they deserve less of your money and attention than the causes above.
Leptin Resistance
Leptin resistance is a real concept in obesity research, but there’s no routine clinical test to diagnose it in an individual. Most research looks at it at a population or laboratory level.
The things that may improve it, such as regular activity and sustainable weight loss, are the same basics that help everything else. So even if it’s part of your picture, the plan doesn’t change.
Estrogen Dominance
“Estrogen dominance” is a term used mostly in functional and alternative medicine, not a recognised mainstream diagnosis. Hormones do change a lot in perimenopause, and that shift is real, but “hormonal imbalance” is too vague to act on without testing.
But a supplement protocol built on this label isn’t a substitute for a proper assessment of your cycle, symptoms and blood work with your doctor.
Inflammation And Omega-3 Fatty Acids
Omega-3 supplements aren't a proven weight-loss tool, even though they have other health benefits. A meta-analysis of randomised trials in overweight and obese adults found that omega-3s might reduce waist circumference and triglycerides but may not effectively reduce body weight, and the authors called the evidence inconclusive.
Eating oily fish twice a week is a sensible part of a healthy diet for women. Just don’t expect a capsule to break a stall.
Gut Health And Bloating
Bloating can make you look and feel heavier without any change in body fat. Salty meals, constipation, a hard workout or your cycle can move the scale by a kilo or more overnight. It’s water and gut contents, not fat. Look at your weekly average, not a single morning.
The Mindset Piece: What Actually Helps
Mindfulness can help with eating behaviours like emotional and binge eating, but its effect on weight itself is mixed. Treat it as a support tool, not the main fix.
The research is split. A 2018 meta-analysis found mindfulness-based programmes reduced weight and obesity-related eating behaviours in people with overweight. A 2022 meta-analysis found they reduced stress in the short term but had no significant effect on weight or BMI.
The honest takeaway: mindfulness is worth doing if stress or emotional eating drives your choices. It won’t override a calorie surplus. Pairing it with the steps below is what makes it count. If stress eating is your pattern, read whether diet can help with emotional eating and stress-related weight gain.
How To Overcome Weight Loss Resistance: A Rule-Out-First Plan
Start with the causes you can measure, fix the fixable ones in order, and only then look at the weaker theories. This saves you months of guessing and money on products you don’t need.
Step 1: Audit Your Intake For 14 Days
Weigh and log everything you eat and drink for two full weeks, weekends included. Given the research on underreporting, this step alone solves the problem for many women. If your true intake is higher than you thought, adjust and give it four more weeks before changing anything else.
Step 2: Ask Your Doctor For The Right Tests
A few routine tests rule out the most common medical causes. Bring a short list to your appointment:
- TSH, to check thyroid function
- A1C or fasting glucose, to check for insulin resistance or prediabetes
- A review of all medications and supplements for weight effects
- Your cycle history and symptoms, if you’re over 40


Step 3: Protect Your Muscle
Strength training while you diet helps you keep muscle, so more of what you lose is fat. In a trial of 160 older adults with obesity on a weight loss programme, lean mass fell by 5% with aerobic exercise alone but only 2 to 3% when resistance training was included, and combined training improved physical function the most.
Aim for two to three strength sessions a week alongside walking or cardio. Our guide to strength training for women over 40 shows you where to start. Pair it with enough protein at each meal; this high-protein diet plan for sustainable weight loss makes that easier.
Step 4: Guard Your Sleep
Make regular, adequate sleep a non-negotiable, especially while you’re in a calorie deficit. Keep the same wake time daily, cut caffeine after midday, and keep your bedroom cool and dark.
Step 5: Measure More Than The Scale
Track waist, strength and how clothes fit alongside a weekly average weight. In midlife especially, body composition can improve while the scale stays stubborn.
Step 6: Ask Whether Medical Treatment Fits You
If you’ve done the steps above for several months and still aren’t losing, ask your doctor whether weight management medication is appropriate. According to the NIDDK, doctors may prescribe these medications when lifestyle changes aren’t enough, usually for adults with a BMI of 30 or more, or 27 or more with weight-related health problems such as high blood pressure or type 2 diabetes.
Medication works alongside healthy eating and activity, not instead of them. Keep strength training and protein high while you use it, so the weight you lose is mostly fat.
Join Our Mailing List
Join thousands of women inside our community and receive our free guide, 10 Actions That Support Permanent Weight Loss — the exact behavioural shifts that make the difference between a two-week attempt and a lasting transformation.
No restriction plans. No guilt. Just what actually works — for real women with real lives.
Weight Loss Resistance Myths vs Facts
Most myths about weight loss resistance promise a hidden cause and a quick fix; the facts point to measurable causes and steady habits.
- Myth: “My metabolism is broken.” Fact: Metabolism adapts to dieting, but in the classic diet-resistance study, metabolic rates were normal.
- Myth: “A supplement will unlock fat loss.” Fact: Omega-3s, for example, haven’t been shown to reduce body weight reliably.
- Myth: “Eating less will always fix it.” Fact: Very aggressive deficits and short sleep increase muscle loss.
- Myth: “If the scale isn’t moving, nothing is changing.” Fact: Body composition shifts in midlife can happen with little weight change.
Ready to stop guessing? Grab our free weight loss guide for women and get evidence-based steps delivered straight to your inbox, so your next month of effort goes into what actually moves the needle.
Related Articles
The Bottom Line
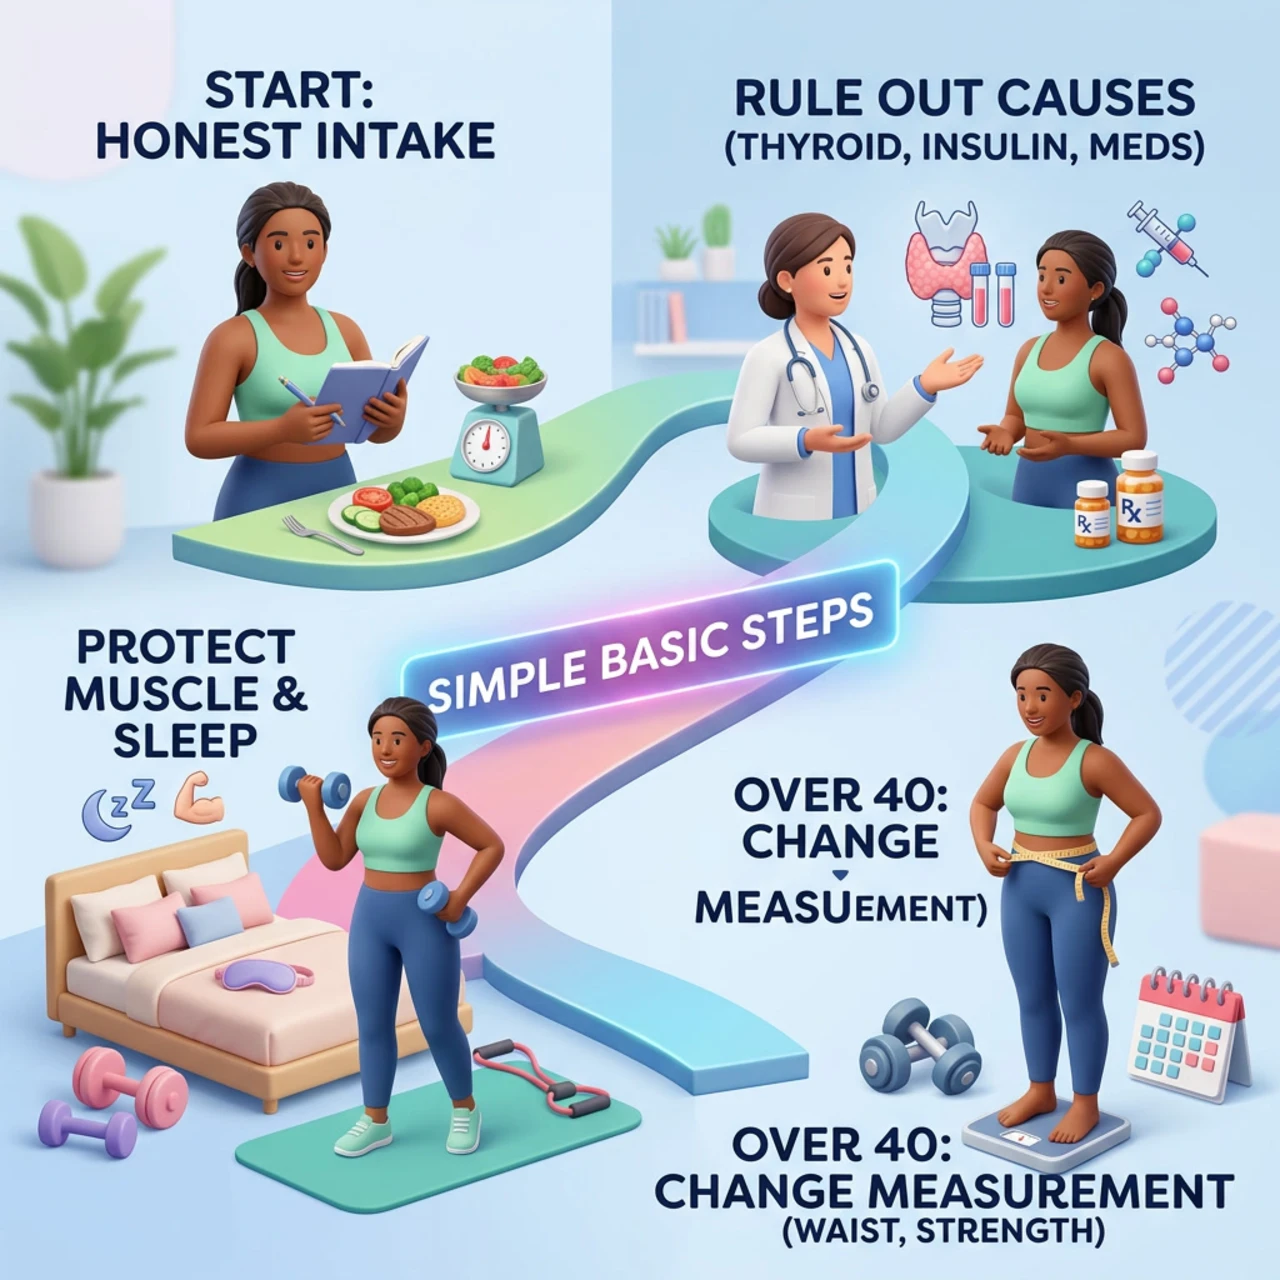
Weight loss resistance is real as an experience, but it’s usually explained by measurable, fixable causes rather than a mystery condition. Start by checking your intake honestly, rule out thyroid problems, insulin resistance and medication effects with your doctor, then protect your muscle and sleep.
If you’re over 40, change what you measure. A stable weight with a smaller waist and stronger lifts is progress. Skip the expensive tests and protocols built on weak evidence until you’ve covered the basics. Most women who work through this list in order find their answer well before they get to the end of it.
Glossary Of Key Terms
FAQ
No, it isn’t an official diagnosis. It describes a pattern of losing little or no weight despite effort. The causes behind it, such as hypothyroidism or insulin resistance, can be real medical conditions.
Ask about a TSH test for thyroid function and an A1C or fasting glucose test for insulin resistance. Also ask your doctor to review your medications for weight effects.
Perimenopause doesn’t stop fat loss, but it changes body composition. Research shows that fat gain speeds up and lean mass drops during the menopause transition, which can make progress feel slower.
Give a carefully tracked plan for at least four to six weeks. Daily weight swings from water and digestion are normal, so compare weekly averages rather than single weigh-ins.
Stress doesn’t block weight loss directly, but it can raise cortisol, disrupt sleep and drive cravings. Those effects make a calorie deficit harder to keep.
Most don’t have strong evidence. Omega-3 supplements, for example, haven’t been shown to reliably reduce body weight in overweight adults. Fix intake, sleep and training first.
Not always. First, check that your tracking is accurate. Very low intakes can increase muscle loss and hunger, so a moderate deficit with strength training usually works better.